
In a chest CT scan, a lung nodule may occupy only a small cluster of voxels. Vessels and airway walls can look much the same, so an early-2000s computer-aided detection system had to find plausible nodules without burying the radiologist in false alarms. The problem reflects a shift in medical image analysis: researchers were asking software to identify, outline, and measure anatomy and disease, not just make scans easier to view.
No single breakthrough settled that work. Progress came through advances in image acquisition, registration, segmentation, computer-aided diagnosis, and evaluation. Digital scans stored in formats such as DICOM were also becoming available to research groups in quantities that made systematic experiments possible.
What made the early 2000s a turning point?
Medical image analysis was hardly new. Researchers had already developed edge detectors, deformable contours, atlas-based methods, and statistical shape models. By the early 2000s, volumetric data were more routinely available, desktop computers were faster, and there was more reason to compare methods on clinical tasks. Multi-detector CT made thin-slice, three-dimensional studies increasingly useful. MRI offered multiple contrasts for examining soft tissue, while digital pathology posed the separate problem of working with very large images.
A stack of slices could not simply be treated as a set of unrelated pictures. Pixel spacing within a slice might differ from the distance between slices, and a patient's position could change between scans. Ignore either fact, and an overlay might look convincing while producing the wrong volume measurement. The decade's advances make more sense as connected parts of a workflow than as isolated classification techniques.
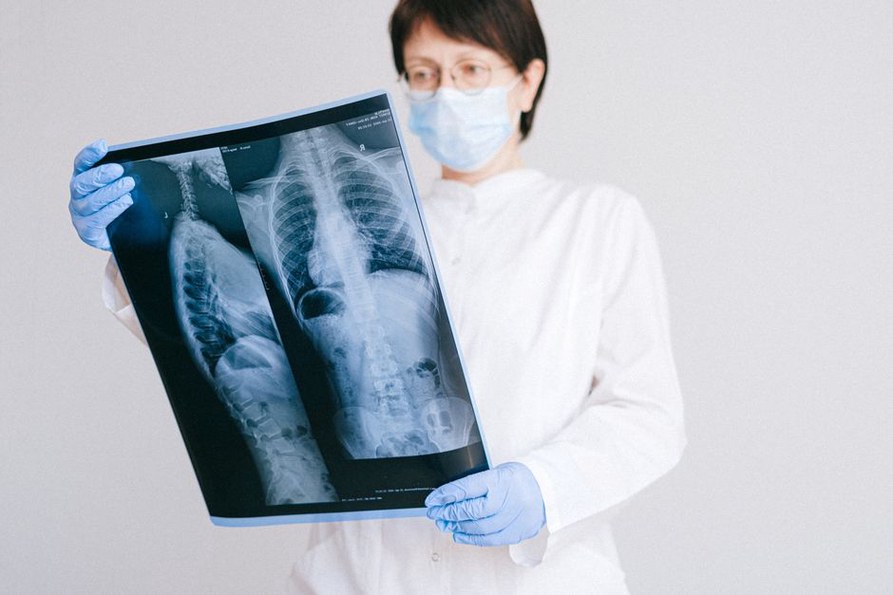
Registration made scans comparable
Image registration estimates how one image should be aligned with another. It mattered when researchers followed tumors over time, combined scans from different modalities, or compared a patient's brain with an anatomical reference. A rigid alignment can shift and rotate an image; an affine one can also scale or shear it. Deformable registration permits local changes, useful when tissue moves or anatomy varies between people.
Intensity-based alignment, including methods based on mutual information, saw wider use. Instead of requiring researchers to mark matching landmarks throughout both scans, these methods searched for an alignment that made the images' intensity patterns statistically compatible. That helped with multimodal scans, where a structure bright in one modality might not be bright in another. Clinical PET/CT scanners, introduced around the start of the decade, made the pairing of functional PET information with CT anatomy especially visible in practice.
But the best numerical score did not necessarily mean the best clinical alignment. A small lesion could remain misplaced, and a deformable warp might not represent plausible tissue motion. Investigators had to check landmarks, anatomical boundaries, and the measurement the alignment was meant to support.
Segmentation moved from outlines to measurable anatomy
Segmentation assigns image regions to structures such as a brain ventricle, an organ, or a tumor. Early-2000s systems often combined image intensities with shape constraints and guidance from an atlas or a user-supplied point. Level-set methods and other deformable models let a boundary evolve around irregular anatomy. Statistical shape models were useful when a structure's expected form was more dependable than its local contrast.
Brain MRI was a prominent test case. FreeSurfer's automated cortical reconstruction and labeling work developed during this period, while FSL and other research toolkits supported more reproducible brain-image pipelines. Researchers could estimate cortical surfaces, tissue volumes, or lesion burden across many subjects without drawing every boundary from scratch. They still had to inspect failures: motion, unusual anatomy, and scanner-dependent contrast could all produce a plausible-looking but incorrect result.
Why the boundary mattered
A misplaced boundary was not just a cosmetic defect. For a small lesion, a few wrongly assigned voxels could change the reported volume and make growth harder to judge. In radiotherapy planning, an outline could affect which tissue was designated as a target or an organ at risk. Those tasks called for different tolerances and different kinds of expert review.
Researchers therefore looked beyond whether a contour appeared neat. They compared automated outlines with expert ones, measured overlap and boundary distance, and examined how much human annotators differed. Expert disagreement could itself be informative: some scans did not support a single clear border. For a parallel account of classification methods in the period, see the development of kernel methods and SVMs in early pattern recognition; those methods were no substitute for clinical validation.
Computer-aided detection targeted specific reading tasks
Computer-aided detection, or CAD, aimed to flag findings a reader might miss. Mammography was an early commercial setting, with systems receiving US regulatory clearance before the 2000s. Research during the new decade expanded to tasks such as finding lung nodules on CT and polyps in CT colonography. These were systems built around a particular modality, anatomical region, and definition of a suspicious finding—not general-purpose diagnostic machines.
A typical system generated a broad set of candidates, then tried to rule out normal structures. In lung CT, it might first identify compact, relatively dense regions, then examine their shape, intensity, and relationship to vessels. Support vector machines were one classification option, alongside rules and other statistical methods. The trade-off was persistent: keeping more true nodules often meant giving the radiologist more false prompts to inspect.
Detection was not diagnosis. A marked nodule was not necessarily malignant, and finding more small abnormalities did not automatically improve patient outcomes. Studies needed to say whether CAD acted as a second reader, how readers were trained to use its prompts, and whether test cases resembled routine clinical work. Accuracy on a selected image set was not the same as benefit in a reading room.
Shared data and challenges changed the evidence
Some of the most consequential progress was organizational. Public research datasets and coordinated evaluations gave groups a firmer basis for comparison. The Lung Image Database Consortium, formed in the early 2000s, worked toward a reference collection of thoracic CT scans with radiologist annotations; the resulting LIDC-IDRI dataset became influential in nodule research. The Retrospective Image Registration Evaluation project, begun earlier, offered a model for checking registration against independent reference information.
These resources also made disagreement harder to ignore. Expert readers did not always agree on whether a finding counted as a lesion or exactly where its edges lay. LIDC preserved annotations from multiple readers rather than imposing one supposedly indisputable outline. A system that differed from one reader was not necessarily wrong; the scan itself might be ambiguous.
How a challenge split and selected its cases mattered as much as how many it included. Putting scans from the same patient in both training and test sets could inflate apparent performance. Results from one scanner or institution might not hold elsewhere. Credible comparisons needed patient-level separation, consistent definitions of findings, and a record of excluded cases—especially as acquisition protocols grew more varied.
What these milestones did—and did not—establish
By the middle of the decade, software could attempt work that had been laborious by hand: aligning three-dimensional studies, estimating anatomical surfaces, proposing lesion locations, and measuring structures across groups of scans. Its success still depended on the task. A brain atlas did not solve lung-nodule detection; a good registration score did not certify a tumor boundary; a CAD prompt did not replace clinical interpretation.
The lasting lesson lay partly in how to describe an experiment. Consider a study reporting a three-milliliter increase in tumor volume. To judge that number, a reader needs to know the imaging protocol, how follow-up scans were aligned, who corrected the contours, and how much the measured volume changes when the boundary is drawn differently. Without that variability, the increase is difficult to interpret.